Flat Fee vs Percentage Billing for Therapists: Compare Costs

The lower-looking billing fee isn’t always the lower-cost choice. In the flat fee vs percentage billing for therapists comparison, a flat fee stays the same as collections change, while a percentage-based fee varies with revenue collected. Hybrid billing combines elements of both.
It makes sense to weigh more than the monthly bill. Each model can create different incentives, shift financial risk, and raise distinct compliance questions. The best fit depends on your practice’s collection patterns, claim workload, and the services included in the billing arrangement.
This article explains how flat-fee, percentage, and hybrid billing work, then compares their costs and tradeoffs with practical calculations. You’ll also see what to examine in an agreement and why the payment structure matters for compliance. The goal is to help you make a clearer decision based on how your practice operates, not just the headline fee.
Key Takeaways
- Compare the billing fee with collections over time, not just a single month, to see when a flat charge and a percentage produce different costs.
- Include claim volume, service scope, and any additional contract charges when calculating the full cost of billing.
- Hybrid and tiered arrangements can combine predictable base costs with charges that change as workload or collections shift.
- Review how each payment model allocates workload and financial risk, then track billing performance with clear, consistent measures.
- Assess compliance before agreeing to percentage-based compensation, since applicable rules can depend on the payer and jurisdiction.
What Is Flat Fee Medical Billing?
A flat-fee arrangement sets a charge for defined billing work; percentage billing ties the charge to collections. In a flat fee vs percentage billing for therapists comparison, the practical difference is how each payment structure responds when claim activity and revenue change.
What services are included in flat-fee versus percentage billing plans for therapists? The pricing model alone doesn’t determine the service list. The agreement defines covered work, exclusions, and how changes in provider count or claim volume affect the arrangement.
A flat charge can make billing costs easier to forecast, but it may stay the same during a slow month. A percentage charge varies with collections, even when claim volume remains steady. That distinction matters when claims are processed in one month but paid in another.
Consider a hypothetical practice with stable collections but a temporary rise in corrected claims. The workload may increase without a corresponding change in collections. Under a flat arrangement, the agreement determines whether the added work is included. Under a percentage arrangement, the fee follows the collections formula, so the agreement should explain how adjustments and reversals affect the calculation.
When choosing between flat fee vs percentage billing for therapists, assess more than average claim volume. Check whether payment timing, seasonal patterns, or changes in clinician participation create a mismatch between billing effort and collections. Focus on how the agreement handles those shifts, rather than assuming one pricing model automatically encourages better claim submission.
| Option | What determines payment | Planning consideration |
|---|---|---|
| Flat fee | Agreed charge for defined work | Review how scope changes affect the charge |
| Percentage | Agreed share of collections | Clarify which payment adjustments count |
Compliance adds another decision point. According to CMS, under 42 CFR 424.73(b)(3), Medicare may pay a billing and collection agent only if specific conditions are met, including that compensation isn’t related to amounts billed or collected or dependent on actual payment collection. This Medicare rule is specific to its stated context; it shouldn’t be treated as a universal rule for every payer or state.
Before choosing, compare the proposed payment method with your practice’s revenue timing, claim workload, and contract terms. You can then judge whether predictable charges or collections-linked payment better fit the way your practice operates.
Evaluating billing costs and value
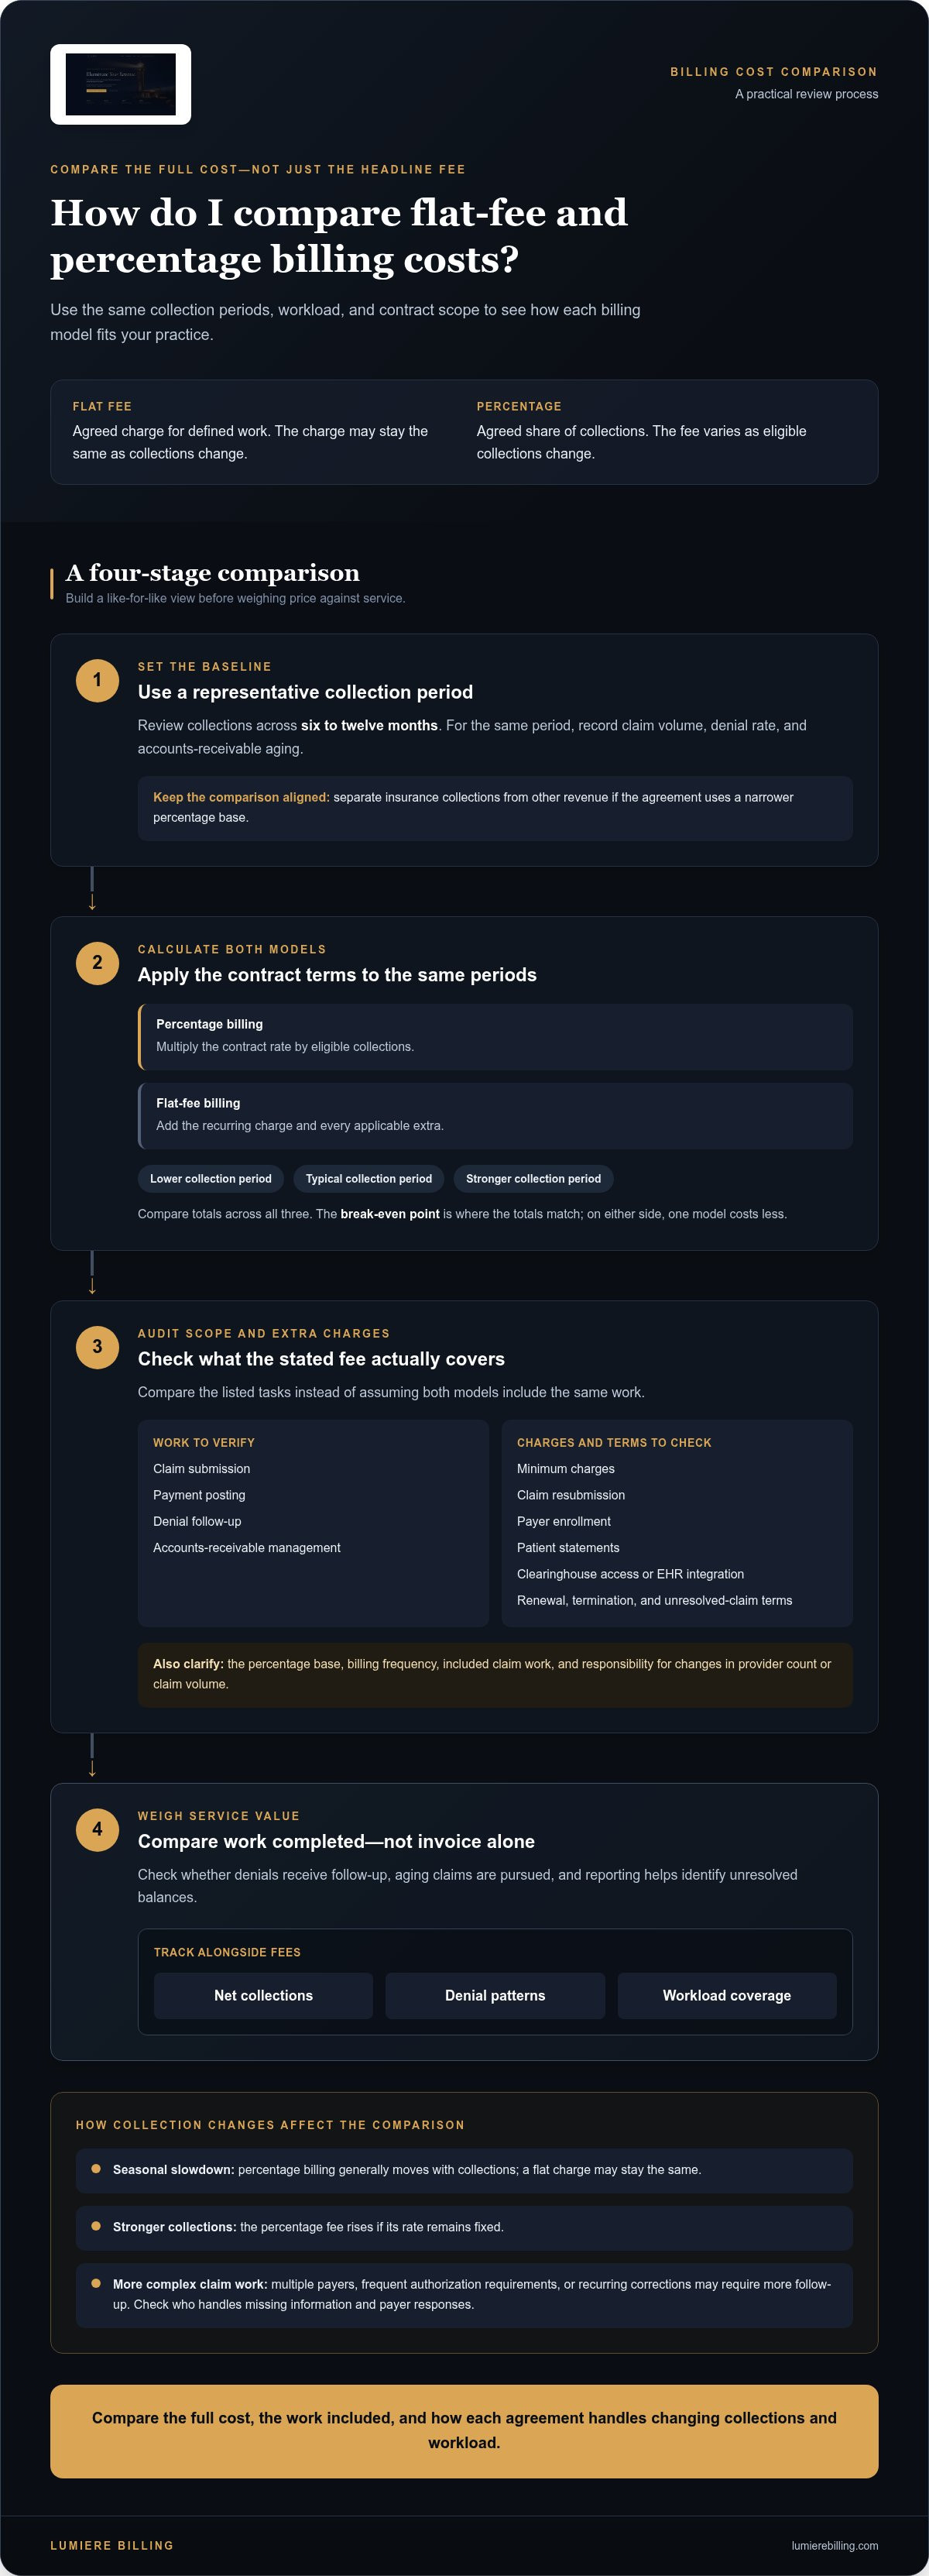
Billing plans may cover claim submission, payment posting, denial follow-up, and accounts-receivable management. The agreement defines the actual scope, so compare each listed task instead of assuming both models include the same work.
Review collections across six to twelve months, then record claim volume, denial rate, and accounts-receivable aging for the same period. This baseline helps distinguish your usual pattern from an unusual monthly fluctuation. Separate insurance collections from other revenue if the agreement calculates its percentage on a narrower base.
Next, calculate each model using the same assumptions. For percentage billing, multiply the contract rate by eligible collections. For a flat fee, add the recurring charge and every applicable extra. Compare totals across lower, typical, and stronger collection periods. The break-even point is where the totals match; above or below it, one model costs less.
Value also depends on the work completed, not just the invoice. Review whether denials receive follow-up, aging claims are pursued, and reporting helps identify unresolved balances. A lower fee may include less work; a higher fee may cover tasks that help limit avoidable revenue leakage. Track net collections and denial patterns alongside fees to assess the practical value.
Complexity changes the calculation. A practice with several payers, frequent authorization requirements, or recurring corrections may need more follow-up than one with a simpler claim mix. Compare the scope with your workflow, including who handles missing information and payer responses. Don’t treat a low headline rate as comparable if the agreement excludes essential tasks.
Read the agreement to understand the full payment structure. Check the percentage base, billing frequency, included claim work, minimum charges, and any separate fees for claim resubmission, payer enrollment, patient statements, clearinghouse access, or EHR integration. Review renewal terms, early termination charges, and responsibility for unresolved claims after the agreement ends. These details can change the total cost beyond the stated fee.
Use this sequence before deciding:
- Match the billing scope to actual practice tasks.
- Calculate both models against the same collection periods.
- Add every contract charge and minimum.
- Compare workload coverage, reporting, and denial follow-up.
For example, if collections fall during a seasonal slowdown, percentage billing generally moves with them, while a flat charge may stay the same. During stronger months, the percentage fee rises if its rate remains fixed. Compare both scenarios with your six-to-twelve-month baseline, then choose the structure that fits your collection pattern and required services.
Hybrid and tiered pricing options
A hybrid contract combines a recurring base charge with a variable component, such as a fee per claim or a percentage of collections. A tiered contract changes its pricing when the practice crosses a defined volume threshold. Both structures can balance predictable expenses with workload, but the agreement must state exactly what triggers each charge.
Common hybrid structures include a base payment for core billing tasks, plus charges for work outside that scope. For example, an agreement might separate routine claim submission from resubmissions, patient statements, or credentialing. Those extras can change the total even when the base fee looks stable.
- Base plus per claim: The practice pays a recurring amount, then an added charge for each claim billed under the contract.
- Base plus percentage: The recurring charge covers defined services, with a variable fee calculated from the agreed collections base.
- Volume tiers: The contract assigns different pricing levels to specified claim volumes or provider counts.
With tiered pricing, volume triggers a price change, so define how claims are counted. Specify whether corrected claims, resubmissions, secondary claims, and claims for each clinician count separately. Without clear definitions, a practice could enter a higher tier because of activity that doesn’t represent more completed billing work.
Scrutinize monthly minimums as well. A minimum can make a low-volume month more expensive than a per-claim calculation suggests. Check whether it applies alongside a base fee, replaces it, or sets a floor for percentage charges.
Separate technology and pass-through costs, too. The agreement should state whether these costs are included, passed through at cost, or billed separately. This distinction matters when comparing plans with different claim volumes and service scopes.
To compare a hybrid or tiered plan, build a simple worksheet from the agreement. List the base charge, percentage formula, monthly minimum, claim-volume thresholds, and separately billed services. Then apply the same historical workload to each item. Include credentialing only if your practice needs it, and identify whether it is billed per payer or bundled. This makes a layered fee easier to calculate.
Choose a structure with triggers that match your actual workload, clearly defined additional services, and a monthly calculation you can understand as claim volume changes.
Billing incentives and risk allocation
A pricing model affects how billing costs change, but it doesn’t determine the quality of the claims work. A percentage-based biller earns more when collections rise, linking compensation directly to collected revenue. A flat-fee biller receives the agreed charge regardless of collections, so the practice carries more cost risk during slow months.
That connection can shape priorities. With percentage billing, collecting eligible claims supports both the practice and the biller’s revenue. With a flat fee, the practice’s charge stays stable, but increased claim volume may not increase the biller’s compensation. Neither model alone guarantees timely submission, thorough denial follow-up, or accurate payment posting.
Risk also depends on what the agreement assigns to each party. If a claim is denied because information is missing, the practice may need to provide records or correct clinical details. If a payer rejects a claim because of a billing error, the agreement should clarify who handles correction and resubmission. Identify who monitors aging claims, follows up with payers, and reports unresolved balances. Clear responsibility helps prevent claims from falling between the provider and billing team.
Track performance with measures that reveal the process, not just its price. Monthly reports should define clean claim rate, denial rate, days in accounts receivable, and net collection rate. A clean claim rate above 95% is presented as a high-performing benchmark, while accounts receivable below 35 days is another benchmark. The listed industry denial-rate benchmark is 5% to 10%. Use consistent definitions, since different counting methods can make the same claims operation appear stronger or weaker.
A hypothetical practice can compare the models by reviewing these measures alongside invoices. If its denial rate rises while claims remain unresolved, check whether the agreement clearly assigns follow-up and correction. If claims move steadily but collections fluctuate, a percentage fee may vary with revenue. These figures describe different issues: operational performance and payment structure.
- For predictable expenses: A flat fee limits monthly cost variation, while the practice absorbs collection swings.
- For shared revenue movement: Percentage billing changes with collections, making the fee more expensive as revenue increases.
- For either model: Define claim ownership, reporting measures, and correction responsibilities in writing.
Choose a model only after matching its incentives to your practice’s workload and risk tolerance. Review claim submission, denials, and aging balances together; no single metric shows whether billing is working well.
Compliance rules for percentage-based billing
A percentage charge ties compensation to a provider’s revenue, so the agreement matters beyond the arithmetic. Compliance depends on the payer, jurisdiction, services, and relationship between payment and collections. Treat the agreement as part of the revenue cycle, not just an administrative pricing choice.
Medicare has a specific rule for billing and collection agents. Under 42 CFR 424.73(b)(3), Medicare may pay an agent only when stated conditions are met. These include compensation that is not related to amounts billed or collected and does not depend on actual payment collection. This Medicare payment rule should not be generalized to every payer or every billing arrangement.
Federal anti-kickback analysis also requires attention to the contract’s details. OIG Advisory Opinion 98-4 addresses conditions under which percentage-based billing contracts may qualify for the personal services and management contracts safe harbor. The opinion does not establish that every percentage arrangement qualifies. Its relevance is the terms and circumstances of the specific arrangement.
State rules can differ. California Business and Professions Code Section 650(b) allows fair-market-value percentage-of-revenue arrangements when supported by a proper fair market value analysis. California law also treats failure to disclose the fee or its basis before treatment begins as unprofessional conduct. A written agreement and clear client-facing fee disclosures therefore address separate compliance considerations.
Fee splitting and referral payments raise professional ethics concerns as well. The APA Ethics Code identifies referral payments or fee splitting as unethical under Code 6.07. Professional ethics codes may treat referral payments or fee splitting as an ethical concern, so distinguish them from ordinary billing compensation. These provisions concern referral payments or fee splitting, not a blanket conclusion about every billing contract.
Before adopting a percentage model, compare the arrangement with relevant payer and state requirements. Focus the review on four points:
- Identify whether the contract involves Medicare, Medicaid, commercial insurance, or another payment source.
- Define the exact revenue base and how compensation is calculated.
- Review any fair-market-value support and required fee disclosures.
- Separate billing compensation from payments for referrals or patient steering.
For Medicaid claims, percentage-based fees may be prohibited in Texas and New York because they can be considered fee-splitting. Some states’ anti-kickback statutes may also restrict biller compensation tied to provider collections. These state-specific issues make the claim type and location important details.
Therapists reviewing a contract can use a Free Billing Audit to examine billing practices and identify areas that need closer compliance review.
Lumiere Billing: Free Billing Audit
Lumiere Billing’s Free Billing Audit is a practical next step if billing costs, claim denials, or unresolved balances make it hard to assess your current process. It can clarify billing activity as you compare pricing structures and consider where revenue cycle management could support your practice.
Schedule a Free Billing Audit, free, no obligation, to examine whether your billing operations align with your workload and collections. For broader operational decisions, Practice Advisory can inform your next steps, while Credentialing & Enrollment addresses payer participation needs.
Contact Lumiere Billing to discuss a Free Billing Audit and your practice’s billing questions.
Make your next billing decision with clarity
Your billing arrangement should support the practice you’re building, not simply reflect how claims were handled in the past. As payer mix, staffing, and administrative needs change, revisit whether the agreement’s scope and incentives still fit your workflow. A thoughtful choice about flat fee vs percentage billing for therapists considers how the billing relationship works day to day, not just how its charge is calculated.
Lumiere Billing can help you examine those operational questions through its Free Billing Audit, Revenue Cycle Management, and Credentialing & Enrollment offerings. The aim is to bring billing activity into focus so your next steps are grounded in your practice’s needs. If you’re ready to discuss your situation, contact Lumiere Billing.
Clearer insight can make the next decision more deliberate. Take the next step when you’re ready.
Frequently Asked Questions
Which Model Works Best for Small Practices?
Neither model fits every small practice; the right choice depends on revenue stability, claim workload, and cash-flow priorities. A solo therapist with seasonal demand may prefer costs that move with collections, while a practice with consistent revenue may value a fixed monthly expense. Consider payer mix and administrative complexity, too. A smaller claim count doesn’t necessarily mean simpler work if denials and follow-up take substantial staff time.
Break-Even Math: When Does Flat Beat Percentage?
A flat fee costs less once collections exceed the break-even point for the quoted percentage. Calculate it by dividing the flat monthly charge by the percentage rate expressed as a decimal. Use the proposed contract figures, then compare projected collections with the result. Below the threshold, percentage billing costs less; above it, flat billing costs less, before additional charges or differences in included services.
How Much Does a Mental Health Biller Cost?
The cost depends on the billing model, included work, claim volume, payer mix, and follow-up required. A percentage-based arrangement changes with collections; flat and per-claim structures depend on contract terms and workload definitions. Lumiere Billing’s Revenue Cycle Management fees are based on a percentage of collections. Credentialing and project work are scoped separately, with a quote based on practice volume and payer mix.
How much should you expect to pay a therapy billing service?
The total reflects the stated billing model and any separately scoped services. Before budgeting, identify whether the agreement covers eligibility checks, payment posting, denial follow-up, and appeals, or assigns some tasks to your staff. Account for changes in claim volume and any contract minimums, too. Lumiere Billing provides a quote after reviewing volume and payer mix; credentialing and project work are scoped separately.
So… How Much Should You Expect to Pay?
Use your contract scope and workload to estimate the cost, rather than relying on a generic figure. List the core billing tasks, expected claims, and any separate project work, then calculate the fee under the proposed model. For percentage-based billing, clarify which collections count and when they’re measured. For other models, identify minimums and extra charges. These details create a more useful budget than the headline rate alone.
Which therapy billing pricing model is cheapest?
The cheapest model is the one with the lowest total cost for your practice’s actual workload and required services. Compare the same period and scope of work, including claim corrections, payer follow-up, reporting, and separately billed services. A low headline charge may be less favorable if core tasks are excluded. Recalculate when provider count, payer mix, or claim volume changes, since those shifts can affect both workload and billing costs.
What does flat-fee billing mean for therapists?
Flat-fee billing means the therapist pays a set charge for the billing services defined in the agreement, rather than a fee calculated from collections. The amount is predictable within the contract’s terms, but check whether it changes with provider count or claim volume. For instance, confirm how the agreement handles added clinicians, corrected claims, and tasks outside the listed scope before forecasting expenses.
What does percentage-based billing mean for therapists?
Percentage-based billing means the billing service’s charge is calculated from an agreed share of collections. The agreement should define which payments count, how adjustments or refunds affect the calculation, and when the fee is assessed. This model links the bill to collected revenue, not simply to the number of claims submitted. Therapists should also consider applicable payer and state compliance requirements before agreeing to collection-based compensation.
Frequently Asked Questions
Neither model fits every small practice; the right choice depends on revenue stability, claim workload, and cash-flow priorities. A solo therapist with seasonal demand may prefer costs that move with collections, while a practice with consistent revenue may value a fixed monthly expense. Consider payer mix and administrative complexity, too. A smaller claim count doesn’t necessarily mean simpler work if denials and follow-up take substantial staff time.
A flat fee costs less once collections exceed the break-even point for the quoted percentage. Calculate it by dividing the flat monthly charge by the percentage rate expressed as a decimal. Use the proposed contract figures, then compare projected collections with the result. Below the threshold, percentage billing costs less; above it, flat billing costs less, before additional charges or differences in included services.
The cost depends on the billing model, included work, claim volume, payer mix, and follow-up required. A percentage-based arrangement changes with collections; flat and per-claim structures depend on contract terms and workload definitions. Lumiere Billing’s Revenue Cycle Management fees are based on a percentage of collections. Credentialing and project work are scoped separately, with a quote based on practice volume and payer mix.
The total reflects the stated billing model and any separately scoped services. Before budgeting, identify whether the agreement covers eligibility checks, payment posting, denial follow-up, and appeals, or assigns some tasks to your staff. Account for changes in claim volume and any contract minimums, too. Lumiere Billing provides a quote after reviewing volume and payer mix; credentialing and project work are scoped separately.
Use your contract scope and workload to estimate the cost, rather than relying on a generic figure. List the core billing tasks, expected claims, and any separate project work, then calculate the fee under the proposed model. For percentage-based billing, clarify which collections count and when they’re measured. For other models, identify minimums and extra charges. These details create a more useful budget than the headline rate alone.
The cheapest model is the one with the lowest total cost for your practice’s actual workload and required services. Compare the same period and scope of work, including claim corrections, payer follow-up, reporting, and separately billed services. A low headline charge may be less favorable if core tasks are excluded. Recalculate when provider count, payer mix, or claim volume changes, since those shifts can affect both workload and billing costs.
Flat-fee billing means the therapist pays a set charge for the billing services defined in the agreement, rather than a fee calculated from collections. The amount is predictable within the contract’s terms, but check whether it changes with provider count or claim volume. For instance, confirm how the agreement handles added clinicians, corrected claims, and tasks outside the listed scope before forecasting expenses.
Percentage-based billing means the billing service’s charge is calculated from an agreed share of collections. The agreement should define which payments count, how adjustments or refunds affect the calculation, and when the fee is assessed. This model links the bill to collected revenue, not simply to the number of claims submitted. Therapists should also consider applicable payer and state compliance requirements before agreeing to collection-based compensation.
Free billing audit
Find out what your billing is really costing you
We'll review your claims, denials and collections and show you exactly where revenue is leaking. Free, no obligation, no contract.
Schedule a Free Billing Audit

